We strengthen how hospitals deliver care – so lifesaving treatment works reliably when it matters most.
Hospital births have risen across sub-Saharan Africa and South Asia. Survival hasn’t kept pace.
The gap between where births happen and where quality care is reliably delivered is where Kybele works.
Kybele strengthens quality of care across the full maternal and newborn journey – from admission to discharge – supporting governments in low-and middle-income countries to embed practical solutions into national health systems.
~80%
Reduction in maternal mortality
OTIP – Ghana IFS independent evalutation
35%
Reduction in perinatal mortality
Stillbirths and newborn deaths Kybele supported facilities, Ghana
Scaled
Neuraxial anesthesia for cesarean delivery and labor
Serbia – regional rollout Kybele supported facilities
25+
Peer-reviewed publications
Independent evidence 15 countries – 4 continents Independent & Kybele-led research
THE PROBLEM
Where births go, deaths follow -
until systems catch up.
The shift to hospitals has changed where survival is decided.
Countries follow a predictable transition – from homes to lower-level facilities, and ultimately to hospitals. Across many countries, most births now occur in hospitals – yet mortality remains high because hospitals often cannot deliver the necessary care when it matters most.
Survival is not determined by access alone.
It is determined by how care works inside the health system.
Complications are predictable. Outcomes are not.
The gap is not whether care exists. It is whether advanced care works – every time.
This is the moment where quality – not access – determines survival.
And where investment has the greatest leverage.
OUR MODEL: THEORY OF CHANGE
Clinical excellence. Deep partnership.
Designed for scale.
01
IDENTIFY AND RESPOND
Targeted clinical improvements convert high-risk moments to safe outcomes
02
INTEGRATE
Process gains embedded in standard care reduce mortality consistency
03
SUSTAIN
Low-cost design enables institutionalization without recurrent external funding
04
SCALE
Government-led scale converts facility gains into national mortality reduction
Kybele supports health systems in low-and-middle income countries to develop, embed and sustain improvements that strengthen the quality of care across the full maternal and newborn journey in hospitals – ensuring risks are identified early, care is delivered safely, and outcomes are continuously improved.
Mother & baby journey
from admission to discharge
Referrals & arrival
Triage & monitoring
Antepartum optimization
Labor & theatre
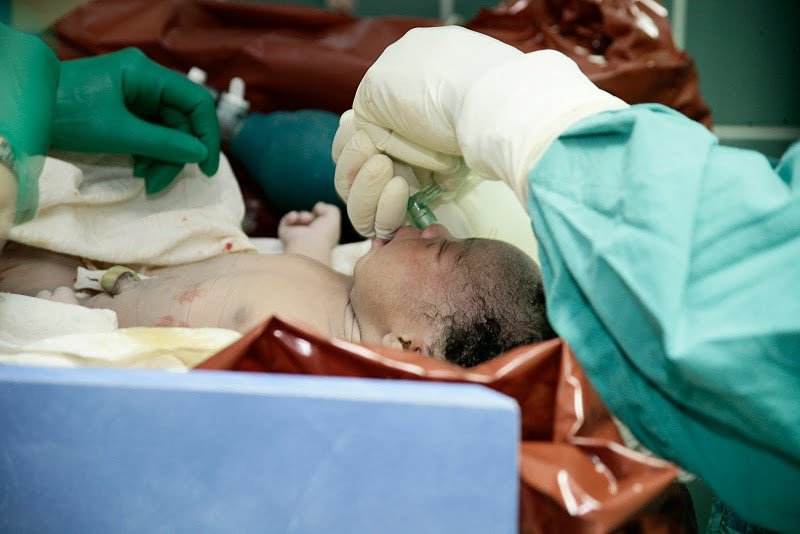
Newborn resuscitation
Postnatal & monitoring
NICU care
Across every stage
Quality improvement * Leadership & governance * Finance * Data & management * Human Resources * Supplies
WHERE WE WORK
14 countries. 4 continents.
A disciplined partnership strategy targeting the moments that determine survival.
Kybele partners where hospital births are rising or already high – and where quality of care improvements have the greatest leverage to save lives at scale.
GHANA
MOZAMBIQUE
BALKANS
UKRAINE
IN-COUNTRY INSTITUTION: KYBELE GHANA
Kybele Ghana is an independent Ghanaian non-profit = the primary in-country partner to the Ghana Health Service. This is not a field office. It is a Ghanaian institution, embedded in the national health system and human infrastructure through which the advanced care work was built, tested and nationally scaled.
GHANA: THE PROOF AT NATIONAL SCALE
Co-designed with the Ghana Health Service.
~80% fewer maternal deaths.
Across low and middle-income countries (LMICs), births are transitioning from homes and lower-level facilities into hospitals, which now account for more than half of births. Despite this, maternal mortality remains high and increasingly, deaths are driven by failures in timely care after arrival at the hospital.
In Ghana, like many LMICs, maternity systems operate on first-come, first-served models rather than clinical urgency, delaying treatment for women with life-threatening complications.
~80%
Reduction in institutional maternal mortality
IFS independent evaluation
110+
GHS Facilities – OTIP national policy
Ghana Health Service, 2024
$0.62
Per birth – absorbed into Ghana’s domestic budget
Program cost data
The Obstetric Triage Implementation Package (OTIP) is a low-cost end-to-end implementation package that insures:
rapid assessment
immediate prioritization
timely management of high-risk cases
650,000
Women reached by OTIP through government-led triage to date
This approach enables sustained implementation, institutionalization, and scale. Nationally scaled by the Ghanaian government – the external evaluation found ~ 80% fewer maternal deaths
An internal evaluation by the Institute for Fiscal Studies (IFS) of the national scale-up shows a casual reduction in institutional maternal mortality of 106 deaths per 100,000 deliveries, relative to a control mean of 124.
That is not an improvement – that is a transformation.